

An ear infection can cause ear pain, pressure, hearing changes, drainage, fever, or a feeling that the ear is blocked. Ear infections can affect different parts of the ear, and the appropriate treatment depends on where the infection occurs and what is causing it.
The most common types include middle-ear infection (acute otitis media) and outer-ear infection (otitis externa or swimmer’s ear). Fluid can also remain behind the eardrum after an infection, causing temporary hearing problems even after the infection itself has resolved. Ear infections are particularly common in children, but adults can develop ear infections as well.
If you or your child has persistent ear pain, drainage, hearing loss, dizziness, or recurrent ear infections, an evaluation by an ear specialist can help identify the cause and determine whether medical or surgical treatment is appropriate.
The ear has three main sections:
- Outer ear: the visible ear and ear canal
- Middle ear: the air-filled space behind the eardrum containing the malleus, incus, and stapes
- Inner ear: the cochlea and balance organs
Different infections affect different parts of the ear and can produce different symptoms.

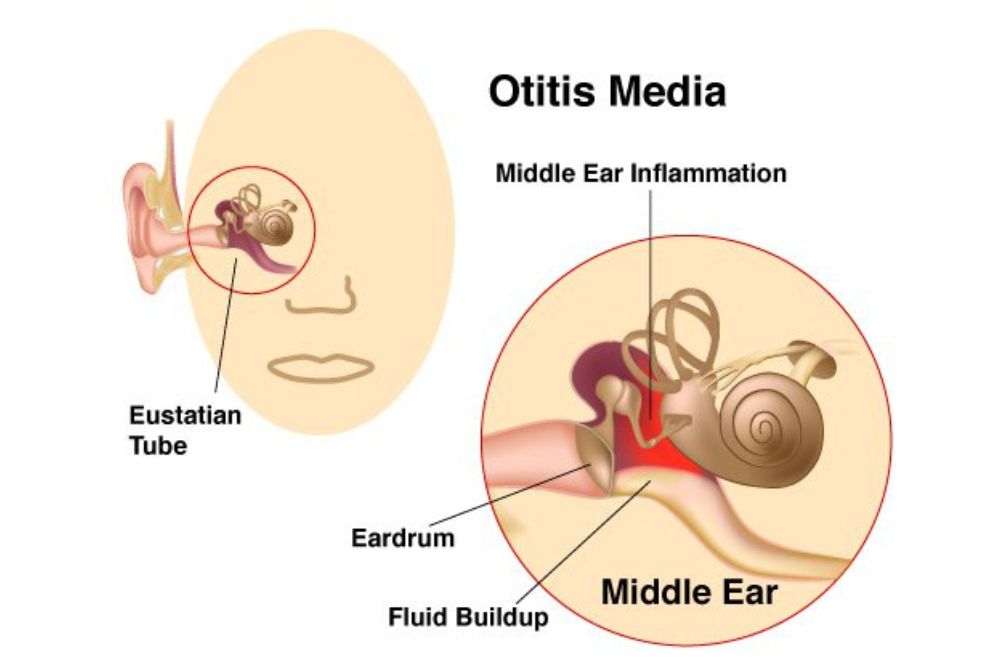
Middle-Ear Infection
A middle-ear infection, medically known as acute otitis media, occurs behind the eardrum. It commonly develops when fluid accumulates in the middle ear and becomes infected.
Outer-Ear Infection
An outer-ear infection, known as otitis externa or swimmer’s ear, affects the skin lining the ear canal. It is different from a middle-ear infection.
Fluid Behind the Eardrum
Otitis media with effusion (OME) occurs when fluid remains in the middle ear without an active infection. It can occur after an ear infection and may cause a sensation of fullness or temporary hearing difficulty.
What Causes Ear Infections?
The causes depend on the type of ear infection.
Causes of Middle-Ear Infections
Middle-ear infections often develop after a cold or other upper respiratory infection. The Eustachian tube connects the middle ear with the back of the nose and throat. It helps ventilate the middle ear and allows fluid to drain.
When the Eustachian tube becomes swollen or blocked, fluid can accumulate behind the eardrum. Bacteria or viruses can then contribute to an infection. Bacteria commonly associated with acute middle-ear infections include Streptococcus pneumoniae and nontypeable Haemophilus influenzae. Viruses that cause respiratory infections can also contribute.
Causes of Outer-Ear Infections
Outer-ear infections can develop when the skin lining the ear canal becomes irritated or damaged and bacteria or fungi multiply. Risk factors can include:
- Swimming or frequent water exposure
- Moisture trapped in the ear canal
- Scratching the ear canal
- Using cotton swabs or other objects inside the ear
- Skin conditions affecting the ear canal
- Trauma to the ear canal
Dr. Sperling’s practice also identifies moisture and water exposure as common factors associated with swimmer’s ear.
Why Are Ear Infections More Common in Children?
Children are more likely than adults to develop middle-ear infections. One reason is anatomical. A child’s Eustachian tubes are smaller and positioned more horizontally, which can make it harder for fluid to drain from the middle ear. A child’s developing immune system can also make it more susceptible to infections.
According to NIDCD, five out of six children experience at least one ear infection by age 3. Children who attend group childcare, have frequent respiratory infections, or are exposed to secondhand smoke may also have increased risk.
What Are the Symptoms of an Ear Infection?
Symptoms depend on the type of infection and the patient’s age. Common symptoms can include:
- Ear pain or an earache
- Ear pressure or fullness
- Muffled hearing
- Temporary hearing loss
- Fever
- Fluid or discharge from the ear
- Irritability in young children
- Trouble sleeping
- Pulling or rubbing the ear
- Itching or irritation
- Dizziness or balance problems
Adults and older children can usually describe ear pain or hearing changes. Babies and toddlers may instead become unusually irritable, have trouble sleeping, or repeatedly pull at the affected ear.
Symptoms of a Middle-Ear Infection
Acute otitis media commonly causes:
- Ear pain
- Pressure or fullness
- Fever
- Reduced or muffled hearing
- Irritability in young children
- Difficulty sleeping
- Fluid behind the eardrum
If the eardrum ruptures, fluid or pus may drain from the ear.
Symptoms of an Outer-Ear Infection
Swimmer’s ear can cause:
- Ear canal pain
- Itching
- Redness
- Swelling
- Ear drainage
- A blocked sensation
- Reduced hearing caused by swelling or debris
- Pain when touching or moving the outer ear
Outer-ear infections can become particularly painful because the infection involves the sensitive skin lining the ear canal.
Can an Ear Infection Cause Hearing Loss?
Yes. Ear infections can cause temporary hearing loss by producing swelling, fluid, or inflammation that interferes with the normal transmission of sound. With a middle-ear infection, fluid behind the eardrum can reduce the movement of the eardrum and middle-ear bones. Hearing may remain reduced even after the infection has improved if fluid continues to be present.
Persistent or recurrent ear infections can also contribute to longer-term hearing problems. If hearing does not return after an ear infection, a hearing evaluation can determine whether fluid, eardrum damage, middle-ear problems, or another hearing disorder is responsible.
Can an Ear Infection Cause Tinnitus or Dizziness?
Yes. Changes in pressure, inflammation, fluid, or hearing associated with an ear infection can sometimes be accompanied by tinnitus, dizziness, or balance problems.
However, significant or persistent dizziness should not automatically be attributed to an ear infection. Other inner-ear or neurologic conditions can cause similar symptoms and may require additional evaluation.
How Are Ear Infections Diagnosed?
Diagnosis begins with a medical history and examination of the ear.
Ear Examination
A physician may use an otoscope or microscope to examine the ear canal, eardrum, and surrounding structures. The examination can help identify:
- Redness or inflammation
- Fluid behind the eardrum
- Bulging of the eardrum
- Perforation
- Ear canal swelling
- Drainage
- Other abnormalities
Dr. Sperling’s current ear-infection page identifies examination with an otoscope or microscope as part of the evaluation.
Tympanometry
Tympanometry measures how the eardrum responds to changes in air pressure. It can help identify middle-ear fluid and other problems affecting middle-ear function.
Audiogram
If hearing loss is present or persists after treatment, an audiogram may be performed to measure hearing sensitivity. A hearing test can help determine:
- How much hearing has changed
- Whether one or both ears are affected
- Whether the hearing loss is conductive or sensorineural
- Whether additional treatment or follow-up is needed
Dr. Sperling’s practice identifies both audiograms and tympanograms as possible components of an ear-infection evaluation.
How Are Ear Infections Treated?
Treatment depends on the type of infection, the patient’s age, the severity of symptoms, and whether complications are present. Treatment may include:
- Observation and follow-up
- Pain management
- Antibiotics when indicated
- Prescription ear drops
- Treatment of underlying Eustachian tube dysfunction
- Treatment of persistent middle-ear fluid
- Ventilation tubes for selected patients with recurrent or persistent problems
- Surgery for chronic ear disease or complications
Do Ear Infections Always Need Antibiotics?
No. Some middle-ear infections improve without antibiotics, particularly in situations where symptoms are mild and the patient can be monitored appropriately. The CDC recommends discussing the treatment approach with a healthcare provider rather than automatically using antibiotics for every ear infection.
For some children with mild acute otitis media, a physician may recommend watchful waiting for a short period to determine whether symptoms improve before antibiotics are prescribed. More severe infections or infections that persist may require antibiotic treatment. The decision should be made by a healthcare professional after examining the ear.
Antibiotics for Ear Infections
When an ear infection is bacterial and antibiotics are appropriate, the medication should be taken exactly as prescribed. Antibiotics do not treat viral infections, and unnecessary antibiotic use can contribute to antibiotic resistance and medication side effects. Do not use leftover antibiotics or someone else’s medication to treat an ear infection.
Ear Drops for Outer-Ear Infections
Outer-ear infections are often treated differently from middle-ear infections. Treatment may involve prescription ear drops designed to treat the infection and inflammation. Keeping the ear dry during treatment can also be important. If the eardrum is perforated or there is a history of ear surgery, the choice of ear drops should be determined by a physician because not every medication is appropriate for every ear. Dr. Sperling’s practice specifically notes this consideration for outer-ear infections.
What Happens If Fluid Remains After an Ear Infection?
Fluid can remain behind the eardrum after an acute middle-ear infection has resolved. This is called otitis media with effusion. A child or adult may no longer have significant pain or fever but may continue to experience:
- Muffled hearing
- Ear pressure
- A plugged-ear sensation
- Difficulty understanding speech
- Temporary conductive hearing loss
In children, persistent middle-ear fluid can affect hearing and may require monitoring. If fluid persists or repeatedly returns, an ear specialist may recommend additional testing and treatment.
When Are Ear Tubes Recommended?
Ventilation tubes, also called ear tubes or tympanostomy tubes, may be considered for selected patients with recurrent ear infections or persistent middle-ear fluid and associated hearing problems. The tubes create an opening through the eardrum that helps ventilate the middle ear and reduce fluid buildup.
Ear tubes are most commonly discussed in children with recurrent or persistent middle-ear problems, but treatment decisions depend on the individual patient’s condition. Dr. Sperling’s suggests that ventilation tubes may be considered when a child has frequent acute otitis media, persistent hearing loss, or chronic middle-ear infection or fluid.
Can Ear Infections Cause Permanent Hearing Loss?
Most uncomplicated ear infections do not cause permanent hearing loss. However, recurrent, persistent, or complicated ear disease can affect hearing over time. Potential problems can include:
- Persistent middle-ear fluid
- Eardrum perforation
- Damage to the middle-ear bones
- Chronic inflammation
- Cholesteatoma
- Conductive hearing loss
Dr. Sperling’s practice notes that untreated or recurrent ear infections can have longer-term effects on hearing and that some chronic cases require surgical treatment. If hearing remains reduced after an infection has resolved, an audiogram can help determine whether the hearing loss is temporary or whether another condition is present.
What Are the Complications of an Ear Infection?
Most ear infections improve with appropriate management, but complications can occur. Potential complications include:
- Persistent hearing loss
- Eardrum perforation
- Chronic middle-ear disease
- Recurrent infections
- Persistent fluid behind the eardrum
- Mastoiditis
- Spread of infection to nearby structures
Mastoiditis is an infection involving the mastoid bone behind the ear and requires prompt medical treatment. Seek medical attention for severe or worsening symptoms, significant ear drainage, persistent hearing loss, or other concerning changes. The CDC specifically recommends medical evaluation for worsening symptoms, ear discharge, hearing loss, or symptoms that persist beyond several days.
When Should You See an Ear Specialist?
Contact a physician if you or your child develops:
- Persistent ear pain
- Hearing loss
- Ear drainage or pus
- Fever associated with ear symptoms
- Recurrent ear infections
- Persistent ear pressure or fullness
- Dizziness or balance problems
- Hearing that does not return after an infection
- Symptoms that continue or worsen despite treatment
For infants younger than 3 months, a fever of 100.4°F (38°C) or higher requires prompt medical attention.
Sudden Hearing Loss Is Different
A sudden decrease in hearing should not automatically be assumed to be an ear infection. Sudden sensorineural hearing loss requires prompt evaluation, particularly when hearing suddenly decreases in one ear. It may feel like the ear is blocked or full, which can make it easy to mistake for congestion or an infection. If hearing suddenly changes, seek prompt medical evaluation rather than waiting to see whether it resolves.
Why Choose Dr. Neil Sperling for Ear Infection Treatment?
If you or your child has an ear infection, an accurate diagnosis is important because middle-ear infections, outer-ear infections, persistent middle-ear fluid, and other ear conditions require different treatments.
Dr. Neil Sperling specializes in disorders of the ear and hearing system in New York City. An evaluation may include an examination with an otoscope or microscope, hearing testing, and tympanometry when appropriate. These tests can help identify infection, fluid, eardrum abnormalities, hearing loss, or other conditions affecting the ear.
For persistent or recurrent ear disease, treatment may include medical management, hearing evaluation, ventilation tubes in appropriate patients, or surgery when chronic ear disease or structural problems require it.
Frequently Asked Questions
Common symptoms of an ear infection include ear pain or earache, a feeling of pressure or fullness in the ear, muffled or temporary hearing loss, fever, fluid or discharge from the ear, irritability in young children, trouble sleeping, ear itching or irritation, and sometimes dizziness or balance problems. Symptoms can vary depending on whether the infection affects the outer, middle, or inner ear.
A middle-ear infection, or acute otitis media, occurs behind the eardrum and often involves fluid buildup that becomes infected. An outer-ear infection, known as otitis externa or swimmer's ear, affects the skin lining the ear canal. The causes, symptoms, and treatments differ between these two types of infections.
Children are more prone to ear infections because their Eustachian tubes are smaller and more horizontal, making fluid drainage from the middle ear more difficult. Additionally, their developing immune systems are more susceptible to infections. Environmental factors like group childcare, frequent respiratory infections, and exposure to secondhand smoke also increase risk.
Yes, ear infections can cause temporary hearing loss due to swelling, fluid, or inflammation that interferes with sound transmission. Fluid behind the eardrum in middle-ear infections can reduce eardrum and middle-ear bone movement. Persistent fluid or recurrent infections may lead to longer-term hearing problems, so hearing evaluation is important if hearing does not improve.
Middle-ear infections often develop after a cold or upper respiratory infection. Swelling or blockage of the Eustachian tube prevents fluid drainage from the middle ear, allowing bacteria like Streptococcus pneumoniae or viruses to infect the trapped fluid. This leads to inflammation and infection behind the eardrum.
Outer-ear infections can result from irritation or damage to the ear canal skin, allowing bacteria or fungi to multiply. Risk factors include swimming or frequent water exposure, moisture trapped in the ear canal, scratching or inserting objects like cotton swabs into the ear, skin conditions affecting the ear canal, and trauma to the ear canal.
Diagnosis involves a medical history and physical examination using an otoscope or microscope to inspect the ear canal and eardrum for redness, swelling, fluid, or perforation. Additional tests like tympanometry can assess middle-ear function, and audiograms may be used if hearing loss is present or persistent to evaluate hearing sensitivity and type of hearing loss.
Treatment depends on the infection type, patient age, symptom severity, and complications. Options include observation and follow-up, pain management, antibiotics when indicated, and prescription ear drops. Addressing underlying causes and complications may also be necessary, and surgical treatment can be considered in recurrent or persistent cases.
Yes, ear infections can sometimes cause tinnitus (ringing in the ears), dizziness, or balance problems due to changes in pressure, inflammation, or fluid affecting the ear. However, persistent or severe dizziness should be evaluated further as it may indicate other inner-ear or neurological conditions.


